❌

Normal view

A viable human lung cancer tissue collection (LCTC) to accelerate translational research

Cancer Treat Res Commun. 2026 Mar 2;47:101162. doi: 10.1016/j.ctarc.2026.101162. Online ahead of print.

ABSTRACT

BACKGROUND: The collection of clinical data and patient tumor specimens in institutional repositories is essential to accelerate translational research in lung cancer, linking laboratory findings with patient outcomes. These resources allow investigators to explore tumor heterogeneity, analyze therapeutic profiles and, more recently, generate patient-derived models of cancer. Given the plethora of therapies in clinical use or under investigation, it is critical to establish tissue collection programs that support the identification of predictive biomarkers of drug sensitivity to define patient subgroups that may benefit from tailored therapeutic strategies. However, access to high-quality viable specimens remains limited.

METHODS: We established a multidisciplinary program -the Lung Cancer Tissue Collection (LCTC) study- to prospectively collect viable human specimens and clinical data. Samples can be collected post-diagnosis and at multiple treatment time points, preserving material for future studies.

RESULTS: In the first 24 months of the LCTC study, we enrolled 158 patients and collected over 700 specimens from patients with lung cancer. EGFR and KRAS mutations were the most frequently identified oncogenic drivers, mirroring frequencies reported in public datasets. We achieved a 60 % success rate in cryopreservation -measured by the proportion of patient-derived organoids growing after tissue thawing and processing- highlighting the feasibility of our program.

CONCLUSIONS: The LCTC biobank captures the molecular and clinical diversity of lung cancer, providing a clinically annotated resource of viable tissue and longitudinal blood specimens. This platform enables patient-derived modeling and multi-omic and functional studies to investigate tumor biology, treatment response, and resistance, supporting biomarker discovery and precision medicine.

PMID:41797251 | DOI:10.1016/j.ctarc.2026.101162

Interorganizational Mechanisms for Developing and Implementing Clinical Decision Support Systems in Primary Care: Exploratory, Qualitative Case Study

Background: Clinical decision support systems (CDSS) have the potential to improve patient safety and reduce costs in primary care. However, CDSS adoption remains limited due to development and implementation challenges. CDSSs are complex interventions involving multiple interacting components that require technological innovation and behavioral and organizational change. Additionally, the primary care context is considered a complex system with high care demand, fragmented structures, and many independent yet interdependent organizations. Established determinant frameworks for implementing and scaling up complex health care interventions support the identification of implementation determinants. However, they offer limited guidance on the underlying processes of these determinants, such as the implementation processes involved in complex interorganizational collaboration in primary care. Objective: This study examined how an interorganizational collaboration in Dutch primary care ( []) achieved an iterative CDSS development and implementation. We aimed to identify the mechanisms that supported the collaboration in overcoming challenges. Methods: We performed an exploratory process-level case study. Data were collected through 15 semistructured interviews. The nonadoption, abandonment, scale-up, spread, and sustainability framework was used to ensure comprehensive topic coverage during the interviews, but not as an analytical framework. We triangulated the interviews with internal and external documents and expert input. Using a thematic, inductive approach, we developed a chronological overview of the collaboration and identified mechanisms offering insights into how GzGr navigated complexity in the development and implementation of CDSS. Results: We identified two mechanisms: (1) enacting an interorganizational value model and (2) iterative, co-creative experimentation. First, GzGr was driven by a coalition of the willing (ie, individuals willing to take an extra step), with shared goals that prioritized collective benefit while respecting organizational values. They established shared principles that translated the broad GzGr mission into concrete CDSS development choices, while also guiding strategic expansion by involving mission-aligned, innovative organizations. Second, after initial prototypes, GzGr established an iterative learning and improvement experimentation for both the technology and the collaboration. This process allowed for rapid feedback, validation of added value, and ongoing refinement. Additionally, this experimentation approached the development and implementation phase as a continuous process involving multistakeholders, supporting both the technology and the collaboration. Conclusions: This study identified 2 mechanisms that sustained interorganizational collaboration and CDSS development. These mechanisms connected collaborative and technical changes across people, technology, and organizational levels, enabling technological viability, stakeholder value, and multilevel support. The mechanisms operated both within and between organizations through iterative cycles of development and implementation. Practical implications include involving multilevel, innovative, and influential stakeholders; maintaining alignment through an orchestrating actor; and adopting an iterative approach between development and implementation. Our findings extend existing determinant frameworks by offering process-level insights into how such mechanisms help overcome challenges in the development and implementation of CDSS within interorganizational collaborations.
  • ✇STAT
  • STAT+: Patient health data as a public utility: A former ARPA-H data chief explains Katie Palmer
    Last year, the Department of Health and Human Services published a sweeping document that described the agency’s approach to real-world data. Historically, health and biomedical data has been intentionally manufactured, the output of carefully designed clinical trials. But in a digitized world, it can instead be mined — and patients’ interactions with the health care system are the natural resource. The Living HHS Open Data Plan, published in July, proposed treating data more like we do other
     

STAT+: Patient health data as a public utility: A former ARPA-H data chief explains

6 March 2026 at 03:00

Last year, the Department of Health and Human Services published a sweeping document that described the agency’s approach to real-world data. Historically, health and biomedical data has been intentionally manufactured, the output of carefully designed clinical trials. But in a digitized world, it can instead be mined — and patients’ interactions with the health care system are the natural resource.

The Living HHS Open Data Plan, published in July, proposed treating data more like we do other natural resources. “At the core” of the plan, it reads, “lies the concept that data is a ‘public utility’ for good that powers scientific advancement, innovation, and progress.” Patients should have access to that utility, HHS argued, but it should also be easier to leverage for research, safety monitoring, and other uses in the public interest. 

On Thursday, a group of researchers, former agency officials, and health data companies continued that call in a policy forum published in Science. If health data is to be treated like a public utility, they write, it should be similarly governed. Like electricity, the system would have to involve customers, local distribution companies, transmission companies, generators, and the government. 

Continue to STAT+ to read the full story…

© Adobe

Systematic Identification of Molecular Signatures Dictating Therapeutic Effects of Clinically First-Line Chemotherapy Regimens for Human Gastric Cancer Patients Based on Organoid Model

MedComm (2020). 2026 Mar 2;7(3):e70656. doi: 10.1002/mco2.70656. eCollection 2026 Mar.

ABSTRACT

Chemotherapy is the mainstay in the treatment of advanced gastric cancer (GC); yet, GC showed diverse responses to first-line chemotherapy regimens and the underlying molecular basis is still not clear. Here, we established a system that combined organoid-based chemotherapy regimen screening and transcriptome-based evaluation to identify underlying molecular signatures of different responses to chemotherapy. We generated 19 GC patient-derived organoids (PDOs) from surgically resected specimens with corresponding histological characteristics of parent tumors and tested all of the five most commonly used first-line chemotherapy regimens. Based on the treatment responses, PDOs were classified into double-sensitive, single-sensitive, and not-sensitive groups. PDOs that responded well to chemotherapy presented high expression levels of the P53 pathway genes and low expression levels of cell proliferative activity genes. Furthermore, the chemotherapy-based tumor classification of GC was established. The GC tumor classification was verified by multi-omics features from the TCGA dataset and public drug response datasets. In conclusion, this study systematically evaluated clinical chemotherapy regimens for GC and identified chemotherapy response-associated molecular signatures based on human GC organoids, which are beneficial to the precise treatments of GC.

PMID:41782964 | PMC:PMC12954136 | DOI:10.1002/mco2.70656

AI Triage in Primary Care: Building Safer and More Equitable Real-World Evidence

Artificial intelligence triage in general practice is developing rapidly within the primary care digital transformation, promising efficiency gains and safety standardization in overwhelmed primary care systems. However, current evidence is drawn from retrospective validations, emergency settings, or vignettes, with scant evaluation of real-world outcomes and almost no equity-stratified safety data, despite known disparities across age, ethnicity, language, and deprivation. From a sociotechnical standpoint, which considers the fit between people, tasks, technology, and organizational context, risks arise not only from algorithmic bias and undertriage but also from human factors, workflow misalignment, governance gaps, and inadequate postdeployment monitoring. We argue that ensuring artificial intelligence triage is safe and equitable requires real-world evaluations in primary care settings, equity-focused performance reporting using theoretically informed frameworks, and rigorous postmarket surveillance. Without these, deployment may widen existing health inequalities rather than moderate them.

Mental Health Professionals’ Perceptions of Benefits and Disadvantages of Telehealth: International Mixed Methods Study

Background: Telehealth has become an integral component of mental health care delivery worldwide. Understanding provider perceptions is essential to guiding its continued implementation. Objective: This international study used quantitative and qualitative methodologies to examine and broaden our understanding of the benefits and concerns related to telehealth for mental health care. Methods: An internet-based survey was conducted during the COVID-19 pandemic between November 11 and December 18, 2020, among mental health professionals, primarily psychiatrists and psychologists, registered with the World Health Organization’s Global Clinical Practice Network. Clinicians completed the survey in 1 of 6 languages (Chinese, English, French, Japanese, Russian, or Spanish). Descriptive statistics and logistic regressions were used to analyze quantitative survey data on concerns and implementation of telehealth. Responses to an open-ended question about providers’ perspectives on the benefits of telehealth were analyzed qualitatively. Results: In total, 847 participants completed the telehealth section of the survey, and 496 provided a response to the open-ended question. Quantitative data on telehealth use and concerns revealed that clinicians’ primary concerns focused on technical issues and clinical effectiveness relative to in-person services, specifically, loss of clinical information (eg, nonverbal behavior) and challenges with establishing a therapeutic alliance. Findings varied by profession, World Health Organization region, and telehealth training and experience. Qualitative data examining benefits fell into 3 major areas: accessibility and reach of mental health services, efficiency and flexibility for clinicians, and enhancement of clinical processes and outcomes. Taken together, findings revealed a trade-off between telehealth benefits and disadvantages. Conclusions: From the perspective of mental health professionals, telehealth practice comes with key challenges and valuable benefits. Findings offer important considerations for the implementation of telehealth systems, including the importance of training and education and balancing trade-offs to optimize care.

Artificial Intelligence Applications in Medical Devices for Personalized Health Care Solutions: Systematic Review

Background: The integration of artificial intelligence (AI) in medical devices is transforming health care by enabling enhanced personalization and precision medicine. AI-driven medical devices can tailor treatments based on individual patient profiles, including genetic data, medical history, and physiological parameters. This advancement holds the potential to refine therapeutic interventions, improve patient outcomes, and streamline health care delivery. However, challenges such as data quality, algorithmic bias, patient privacy, and regulatory complexities hinder the full realization of AI-driven personalization. By 2030, the global AI in health care market is projected to exceed US $187.95 billion, growing at a compound annual growth rate of 37% from US $15.1 billion in 2022. Objective: This review aims to explore the scope and impact of AI-driven personalization in medical devices. It seeks to analyze key technological innovations that have enabled AI integration, identify the critical challenges impeding progress, and evaluate strategies to address these challenges. Additionally, it highlights future research directions and innovation opportunities in this evolving field. Methods: A systematic review was conducted, drawing from scholarly literature, industry analyses, and regulatory advisories. Relevant studies and case examples were analyzed to assess the current applications of AI in medical devices, the barriers to its implementation, and best practices for overcoming these barriers. Ethical, technical, and regulatory considerations were also examined. The review included studies published between 2016 and 2023, covering over 100 peer-reviewed articles and reports. Results: The review highlights significant advancements in AI-driven medical devices, including applications in diagnostics, treatment personalization, wearable health monitoring, and smart prosthetics. AI-based diagnostic tools have achieved up to 98.88% accuracy in multiclass disease classification from X-ray images and 95% accuracy in insulin injection site recognition. It identifies key challenges such as data security risks, algorithmic biases, regulatory constraints, and integration issues with existing health care infrastructures. Currently, more than 70% of clinical decisions rely on diagnostic tests, yet AI-driven automation could reduce diagnostic delays by up to 50%. Several strategies, including improved data validation techniques, regulatory frameworks for AI approval, and ethical guidelines, were found to be effective in mitigating these challenges. Case studies demonstrate how AI has enhanced medical device functionality and patient outcomes. Conclusions: AI-driven personalization in medical devices holds immense potential to revolutionize health care, offering more precise, adaptive, and patient-centered solutions. However, successful implementation requires addressing technical, ethical, and regulatory challenges. Emerging technologies such as quantum computing could improve AI-driven medical diagnoses by 10‐20 times in processing efficiency, while blockchain-based patient data management could reduce security breaches by more than 30%. This review serves as a valuable resource for researchers, health care professionals, policymakers, and industry leaders, fostering informed discussions and guiding future advancements in AI-enabled personalized medicine.

Architecting Trust in Artificial Epistemic Agents

arXiv:2603.02960v1 Announce Type: new Abstract: Large language models increasingly function as epistemic agents -- entities that can 1) autonomously pursue epistemic goals and 2) actively shape our shared knowledge environment. They curate the information we receive, often supplanting traditional search-based methods, and are frequently used to generate both personal and deeply specialized advice. How they perform these functions, including whether they are reliable and properly calibrated to both individual and collective epistemic norms, is therefore highly consequential for the choices we make. We argue that the potential impact of epistemic AI agents on practices of knowledge creation, curation and synthesis, particularly in the context of complex multi-agent interactions, creates new informational interdependencies that necessitate a fundamental shift in evaluation and governance of AI. While a well-calibrated ecosystem could augment human judgment and collective decision-making, poorly aligned agents risk causing cognitive deskilling and epistemic drift, making the calibration of these models to human norms a high-stakes necessity. To ensure a beneficial human-AI knowledge ecosystem, we propose a framework centered on building and cultivating the trustworthiness of epistemic AI agents; aligning AI these agents with human epistemic goals; and reinforcing the surrounding socio-epistemic infrastructure. In this context, trustworthy AI agents must demonstrate epistemic competence, robust falsifiability, and epistemically virtuous behaviors, supported by technical provenance systems and "knowledge sanctuaries" designed to protect human resilience. This normative roadmap provides a path toward ensuring that future AI systems act as reliable partners in a robust and inclusive knowledge ecosystem.
  • ✇InfoQ
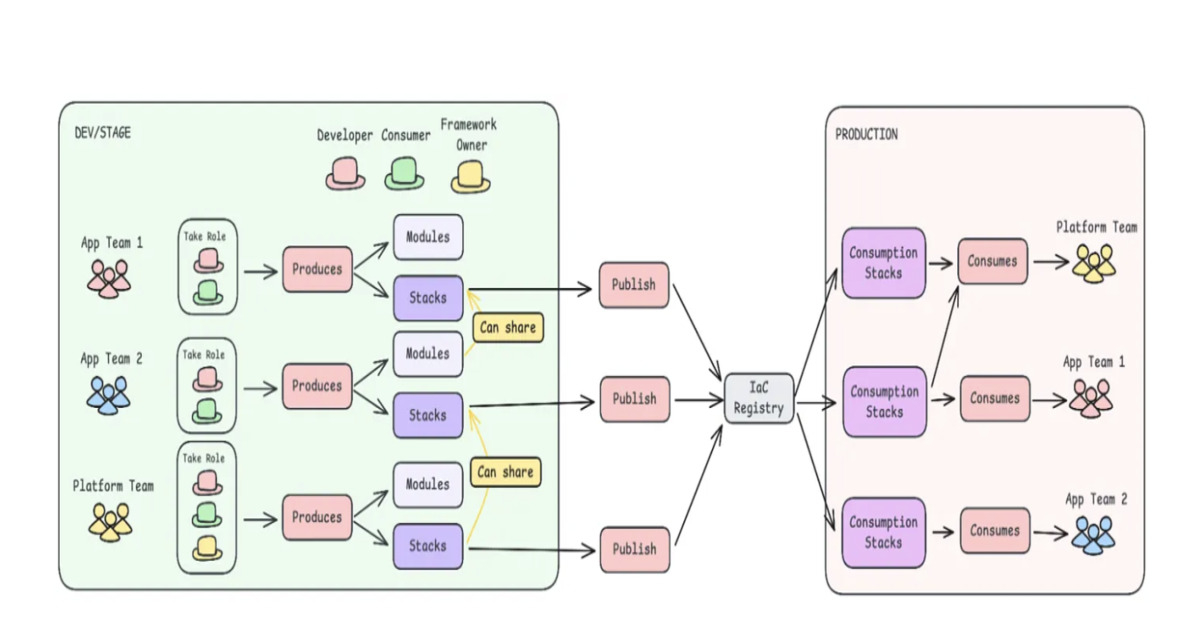
  • From Central Control to Team Autonomy: Rethinking Infrastructure Delivery Leela Kumili
    Adidas engineers describe shifting from a centralized Infrastructure-as-Code model to a decentralized one. Five teams autonomously deployed over 81 new infrastructure stacks in two months, using layered IaC modules, automated pipelines, and shared frameworks. The redesign illustrates how to scale infrastructure delivery while maintaining governance at scale. By Leela Kumili
     

From Central Control to Team Autonomy: Rethinking Infrastructure Delivery

3 March 2026 at 23:01

Adidas engineers describe shifting from a centralized Infrastructure-as-Code model to a decentralized one. Five teams autonomously deployed over 81 new infrastructure stacks in two months, using layered IaC modules, automated pipelines, and shared frameworks. The redesign illustrates how to scale infrastructure delivery while maintaining governance at scale.

By Leela Kumili

Unraveling pancreatic ductal adenocarcinoma at single-cell resolution with spatial insights: From mechanisms to clinical translation

Cancer Lett. 2026 Feb 28;645:218391. doi: 10.1016/j.canlet.2026.218391. Online ahead of print.

ABSTRACT

Pancreatic ductal adenocarcinoma (PDAC) remains one of the most lethal cancers, characterized by pronounced cellular heterogeneity, a dense desmoplastic stroma, and a highly immunosuppressive tumor microenvironment (TME). Recent advances in single-cell RNA sequencing (scRNA-seq) have reshaped our understanding of PDAC by characterizing its cellular composition at single-cell resolution. These studies have uncovered complex TME networks involving T cells, myeloid populations, fibroblasts, and malignant epithelial cells, and have provided mechanistic insights into immune evasion, metastatic progression, and therapeutic resistance. Collectively, these findings depict PDAC as a dynamic and interactive ecosystem driven by cellular interactions. In this review, we systematically summarize recent scRNA-seq-based studies addressing PDAC heterogeneity, tumorigenesis, immune remodeling, therapeutic resistance and biomarker discovery. We further discuss integrative single-cell and spatial multi-omics approaches to map the TME of PDAC, providing a framework for understanding PDAC biology at single-cell and spatial resolution.

PMID:41771343 | DOI:10.1016/j.canlet.2026.218391

Spatial transcriptomics reveals the mechanistic role of lactate metabolism in the pancreatic ductal adenocarcinoma microenvironment

Front Immunol. 2026 Feb 13;17:1743187. doi: 10.3389/fimmu.2026.1743187. eCollection 2026.

ABSTRACT

BACKGROUND: Pancreatic ductal adenocarcinoma (PDAC), an aggressive cancer with poor prognosis, poses major challenges owing to late diagnosis and limited response to current therapies. However, the identification of candidate drugs through multi-omics analyses and therapeutic peptides targeting key molecular pathways may provide improved outcomes. Although lactate metabolism is a critical factor in tumor progression, affecting cell proliferation, metastasis, and immune evasion, its role in PDAC-particularly within the tumor microenvironment, remains underexplored.

OBJECTIVES: This study investigated lactate metabolism in PDAC using high-throughput transcriptomic sequencing and single-cell transcriptomic analysis.

METHODS: Lactate metabolism-related gene expression was analyzed in tumor cells and their microenvironment, and correlations with patient prognosis were determined. Additionally, a machine learning-based prognostic model was established to identify lactate metabolism biomarkers for early diagnosis and personalized therapy.

RESULTS: Lactate metabolism significantly impacted the survival of patients with PDAC (n = 92; log-rank test, p < 0.05). Single-cell RNA and spatial transcriptomics analyses of 50, 795 cells from 8 PDAC samples revealed that 521 malignant cells exhibited hyperactive lactate metabolism (AUCell score comparison, p < 0.001). A prognostic model constructed from lactate metabolism-related genes using ensemble machine learning (StepCox + Enet, α = 0.5) effectively stratified patients into high- and low-risk groups across multiple cohorts (ICGC: n = 92; GSE28735: n = 45; GSE62452: n = 69; GSE183795: n = 139; all log-rank p < 0.05). Key prognostic genes identified included lysozyme (LYZ) and polymeric immunoglobulin receptor, which were significantly associated with patient survival (univariate Cox regression, p < 0.05). These genes may serve as clinical biomarkers of PDAC.

CONCLUSIONS: This study provides insights into PDAC metabolic features and highlights lactate metabolism as a potential therapeutic target. The identified biomarkers could facilitate early diagnosis and improve treatment strategies, ultimately enhancing patient outcomes.

PMID:41766855 | PMC:PMC12946077 | DOI:10.3389/fimmu.2026.1743187

The Transformative Potential of Liquid Biopsies and Circulating Tumor DNA (ctDNA) in Modern Oncology

Diagnostics (Basel). 2026 Feb 9;16(4):523. doi: 10.3390/diagnostics16040523.

ABSTRACT

Background: Liquid biopsy, particularly through the analysis of circulating tumor DNA (ctDNA), represents a significant advancement in oncology. Unlike traditional tissue biopsies, ctDNA offers a minimally invasive, real-time approach to cancer management. It has demonstrated considerable potential in early cancer detection, monitoring of therapeutic responses, and assessing minimal residual disease (MRD) to predict recurrence. By enabling comprehensive molecular profiling through a simple blood test, ctDNA supports the core principles of precision oncology, facilitating more personalized and adaptive treatment strategies. Methods: In the following article we describe the recent developments focused on refining ctDNA detection assays to improve sensitivity and specificity. Advanced technologies, including next-generation sequencing (NGS) and digital PCR, are commonly employed. The integration of artificial intelligence (AI) and multi-omics approaches-such as combining genomic, epigenomic, and transcriptomic data-has further enhanced the analytical power of ctDNA assays. Results: Emerging evidence shows that ctDNA-based liquid biopsy enables dynamic, real-time tracking of tumor evolution and therapeutic resistance. Clinical studies have demonstrated its efficacy in detecting early-stage cancers, guiding treatment selection, and predicting relapse with higher accuracy than some conventional methods. Moreover, AI-enhanced algorithms have improved signal detection, allowing for more precise and earlier identification of actionable mutations and MRD. Conclusions: ctDNA analysis via liquid biopsy is poised to revolutionize cancer care by offering a non-invasive, precise, and adaptive tool for tumor characterization and monitoring. Although obstacles remain-particularly regarding assay sensitivity, standardization, and economic feasibility-ongoing technological innovations and multi-omics integration are rapidly advancing its clinical viability. With continued progress, ctDNA-based liquid biopsy is likely to become a cornerstone of routine oncology practice.

PMID:41750672 | PMC:PMC12938931 | DOI:10.3390/diagnostics16040523

3D, multi-omic imaging reveals molecular biomarkers of the pre-metastatic niche in lung cancer

bioRxiv [Preprint]. 2026 Feb 18:2026.02.18.706515. doi: 10.64898/2026.02.18.706515.

ABSTRACT

The recurrence rate following complete surgical resection of primary non-small cell lung cancer is as high as 55%, yet no approach currently exists to evaluate the risk of local recurrence. The premetastatic paradigm is the recognition that metastasis is preceded by reprogramming naïve tissues to prime a microenvironment for tumor cell survival and subsequent reactivation. Identification of biomarkers of the pre-metastatic niche would allow us to evaluate a patient's risk of local relapse in the normal lung parenchyma surrounding the resected tumor. We designed a workflow incorporating in vivo modelling, radiology, and deep learning-guided three-dimensional (3D) imaging, spatial proteomics, and transcriptomics to identify previously unreported signals associated with the early transformation of the lung parenchyma announcing regional metastasis. We curated biorepository spanning timepoints before and after resection of primary Lewis Lung Carcinoma (LLC) tumors. Using radiology and cellular resolution 3D histology, we calculated the number and distribution of metastases in mouse lungs and developed an algorithm to guide placement of spatial proteomics and transcriptomics to regions containing early micro-metastases and the pre-metastatic microenvironment. Molecular and tissue features associated with presence, size, and location of metastases guided the identification of both myeloid (F4/80) and senescent (p16/p21) cell signatures in the premetastatic and metastatic environments. Finally, multiparametric flow cytometry of metastatic lungs in a senescence reporter GEMM (tdTomato-p16 INKA mice) resolved senescent cells including alveolar macrophages as the cellular phenotypes associated with these early premetastatic signatures. Altogether, this work highlights a novel AI-assisted approach for detection of biomarkers of tissue remodeling during lung cancer invasion.

PMID:41756853 | PMC:PMC12934922 | DOI:10.64898/2026.02.18.706515

Exploration of multi-omics liquid biopsy approaches for multi-cancer early detection: The PROMISE study

Innovation (Camb). 2025 Aug 6;7(1):101076. doi: 10.1016/j.xinn.2025.101076. eCollection 2026 Jan 5.

ABSTRACT

Although circulating cell-free DNA (cfDNA) methylation has emerged as the mainstream approach in multi-cancer detection blood tests (MCDBTs), the potential of integrating proteins and mutations, to enhance its performance remains unclear. The PROMISE study (NCT04972201) was conducted to investigate the feasibility of a multi-omics integration strategy in MCDBTs across nine types of cancers in head and neck (excluding nasopharynx), esophagus, lung, stomach, liver, biliary tract, pancreas, colorectum, and ovary. Blood samples were prospectively collected from 1,706 participants (840 non-cancer; 866 cancer) and then randomly divided into training and validation sets. The complementarity between various omics were investigated, and specific omics features were carefully selected for further multimodal model construction. The methylation-based classifier outperformed both the mutation-based and protein-based classifiers. As 95.0% of cancer cases detected by the mutation-based classifier were simultaneously identified by the methylation-based classifier, while 14.0% of the protein-positive samples were missed, protein markers may provide complementary value to the methylation-based classifier. Compared with the methylation-based classifier, the multimodal classifier combining methylation and protein features exhibited an improved sensitivity of 75.1% (95% confidence interval [CI], 69.3%-80.3%) at the same specificity of 98.8% with the accuracy of top predicted origin (TPO1) of 73.1% (95% CI, 66.2%-79.2%). Notably, the TPO1 accuracy reached 100% in liver and ovarian cancers with negative results of the methylation-based classifier. Collectively, these data suggest that the integration of protein markers in the multimodal classifier can offer additional benefits to the methylation-based classifier, particularly in identifying liver and ovarian cancers.

PMID:41737326 | PMC:PMC12925926 | DOI:10.1016/j.xinn.2025.101076

Metabolic dysregulation: Its role in diabetes mellitus and cancers

Mol Aspects Med. 2026 Feb 23;108:101461. doi: 10.1016/j.mam.2026.101461. Online ahead of print.

ABSTRACT

Diabetes mellitus (DM) is a significant risk factor for several cancers, particularly cancers of the liver, pancreas, and endometrium. This review aims to understand the connections between diabetic pathophysiology and cancer biology. We synthesize how core metabolic disturbances-hyperinsulinemia, hyperglycemia, and inflammation-promote tumorigenesis by dysregulating canonical oncogenic pathways such as IGF-1 signaling, DNA damage repair, and immunometabolism. Subsequently, we focus on how key molecular integrators-such as p38 MAPK, Wnt/β-catenin, and the AGEs-RAGE axis-mediate metabolic stress to confer proliferative and invasive advantages to tumor cells. However, a direct translational application of these mechanisms, particularly in the context of repurposing antidiabetic drugs for cancer therapy, remains challenging due to inconsistent clinical outcomes. To address this gap, we suggest that a fundamental shift in approach is required. We propose that future research must move beyond simple pathway categorization and instead utilize spatial analysis techniques to reveal how diabetic metabolites reshape the tumor microenvironment (TME). By integrating single-cell and spatial omics technologies, the field can begin to map the precise cellular niches within tumors where diabetic metabolites exacerbate malignant progression and foster treatment resistance. This perspective is essential for developing targeted strategies to mitigate cancer risk and improve outcomes for the expanding population of patients with DM and cancer.

PMID:41734405 | DOI:10.1016/j.mam.2026.101461

AI and Wearables for Early Detection of Cognitive Impairment and Dementia: Systematic Review

Background: Traditional cognitive screening relies on episodic clinical assessments and may miss early changes preceding cognitive impairment and dementia. Wearable and mobile health technologies enable continuous monitoring of sleep, physical activity, and circadian rhythms, generating digital biomarkers that may support scalable early detection and prevention. However, current evidence remains fragmented across devices, analytic approaches, and cognitive outcomes. Objective: This study synthesizes and critically evaluates recent evidence on wearable devices for early detection and prevention of cognitive impairment and dementia, focusing on device categories, cognitive outcomes, analytic approaches, and prevention relevance. Methods: We searched PubMed, Scopus, ACM Digital Library, and SpringerLink for peer-reviewed studies published between January 2020 and December 1, 2025. Eligible studies included human participants with a mean age ≥50 years, continuous wearable-derived data collected for ≥24 hours, and validated cognitive outcomes; reviews, protocols, smartphone-only studies, and pharmacological interventions were excluded. Two reviewers independently screened studies, extracted data, and assessed risk of bias using the Appraisal Tool for Cross-Sectional Studies, Newcastle-Ottawa Scale, Cochrane Risk of Bias tool, and Quality Assessment of Diagnostic Accuracy Studies-2. Owing to substantial heterogeneity in devices, outcomes, and analytic methods, quantitative meta-analysis was not feasible; a structured narrative synthesis was conducted in accordance with PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) 2020 guidance. This study was not prospectively registered. Results: We included 49 studies, with sample sizes ranging from 14 to 91,948 participants (>200,000 total) and a median sample size of 145. Most used research-grade actigraphy (43/49, 87.8%), while fewer used commercial wearables (7/49, 14.3%). Cognitive outcomes most frequently relied on global screening instruments, including the Mini-Mental State Examination (18/49, 36.7%), followed by ICD-10 (International Statistical Classification of Diseases, Tenth Revision)–based clinical diagnoses (7/49, 14.3%) and the Montreal Cognitive Assessment (7/49, 14.3%). Analytic approaches were predominantly statistical (36/49, 73.5%), with fewer studies applying machine learning (7/49, 14.3%) or deep learning methods (6/49, 12.2%). Statistical analyses linked disrupted sleep, circadian rhythm fragmentation, and irregular activity patterns to worse cognitive outcomes, with modest-to-moderate effect sizes. Machine learning and deep learning approaches reported classification performance with area under the curve values between approximately 0.70 and 0.95. Approximately one-quarter of the studies (13/49, 26.5%) addressed early detection or prevention through longitudinal risk estimation or predictive modeling. Key limitations included small sample sizes, short monitoring durations, and limited external validation. Conclusions: Wearable-derived behavioral markers show promise for early risk stratification. This review advances the field by shifting from descriptive associations toward a digital phenotyping framework evaluating artificial intelligence–driven prediction in the preclinical window. Unlike prior reviews focused on established dementia, it differentiates direct predictive evidence from indirect correlational findings and critically assesses methodological maturity. Continuous, passive monitoring may enable scalable detection of subtle behavioral changes, supporting earlier and more personalized risk reduction strategies. Trial Registration:

Preliminary Exploration of Fluvastatin Inhibiting Proliferation, Migration and Invasion of Lung Cancer Cells and Reversing Paclitaxel Resistance: Mechanism Exploration Based on Multi-Omics Analysis

23 February 2026 at 19:00

Drug Des Devel Ther. 2026 Feb 16;20:579427. doi: 10.2147/DDDT.S579427. eCollection 2026.

ABSTRACT

BACKGROUND: Lung cancer is one of the leading causes of cancer-related deaths, among which NSCLC accounts for approximately 80-85% of all lung cancer cases. Paclitaxel (TAX) is a commonly used chemotherapeutic drug, but it is easy to cause drug resistance. Fluvastatin has anti-cancer potential, but the mechanism of its reversal of drug resistance is unclear.

METHODS: The study was divided into four groups: the A549 control group, the A549/Tax control group, the A549 Fluvastatin-treated group, and the A549/Tax Fluvastatin-treated group. CCK-8, Transwell, and flow cytometry assays were used to detect fluvastatin's effects on cell proliferation, migration, invasion, and apoptosis. Transcriptomics, proteomics, and acetylomics were combined to explore the potential molecular mechanisms.

RESULTS: The preliminary results showed that fluvastatin inhibited the proliferation, migration and invasion of A549 and A549/Tax cells and promoted their apoptosis. Multi-omics analysis revealed that a large number of differentially expressed molecules were detected in both the A549-Fluvastatin vs A549-NC group and the A549/Tax-Fluvastatin vs A549/Tax-NC group, and these molecules were significantly enriched in multiple biological processes and signaling pathways. This suggests that fluvastatin may exert its effects through the synergistic regulation of multiple molecules and pathways. Integrated multi-omics analysis identified several key molecules (for example, HMGCR, RDH11, HSPB1) and acetylated protein-target gene pairs (for example, P09874-BCL2, P42224-PTGS2, P04150-CCND3), which may mediate the antitumor mechanism of fluvastatin.

CONCLUSION: This study indicates that fluvastatin has the potential to reverse TAX resistance in lung cancer, and the results of multi-omics analysis provide a theoretical basis for the exploration of potential therapeutic targets in the future.

PMID:41728357 | PMC:PMC12922964 | DOI:10.2147/DDDT.S579427

❌